Mastiff Hip Dysplasia Prevalence: What the Statistics Do and Do Not Tell You
Quick answer
Why do published hip dysplasia rates vary so much?
They come from voluntary submissions, use different scoring systems, are taken at different ages, and count radiographic change rather than clinical pain. All four inflate or deflate the figure.
Every published hip dysplasia percentage answers a slightly different question from the one you are asking.
Prospective Mastiff buyers comparing breeders and trying to evaluate health claims, and current owners trying to work out whether their dog's risk is high, average, or already known.
Important reminder
This guide is not medical advice. If your dog shows pain, sudden behavior change, or worsening symptoms, consult a licensed veterinarian.
Some links may be affiliate links. We may earn a commission at no extra cost to you. We only suggest products we believe are helpful for dog owners.
We research and check what we publish, but we do not warrant that any figure, date, price, or statement is accurate, complete, or current, and we accept no liability for any loss, cost, injury, or other harm arising from the use of this site. Use it as one reference among several. You remain responsible for your own decisions and for your dog's care - confirm anything that matters with a licensed veterinarian or another qualified professional before you act on it. Full disclaimer.
What this problem looks like
Hip dysplasia prevalence figures are widely quoted and poorly understood. They derive from voluntary screening registries, use incompatible grading systems, are recorded at an age before most arthritis develops, and count radiographic appearance rather than pain. For a prospective Mastiff owner the useful information is not the breed percentage but the documented screening history of the specific line.
Common triggers
Buying from a breeder who does not screen breeding stock
Relying on a verbal health assurance rather than a dated certificate
Comparing scores issued under different grading schemes as if equivalent
Assuming a clear evaluation at two years covers the whole lifespan
Feeding a puppy for maximum growth rate during skeletal development
Hip dysplasia is listed among the Mastiff's documented health issues and affects numerous large breeds as well as some small ones. Radiographic changes are considerably more common than visible lameness in any affected breed, which is why prevalence discussions and owner experience often seem to disagree.
Why this happens
Breed factors
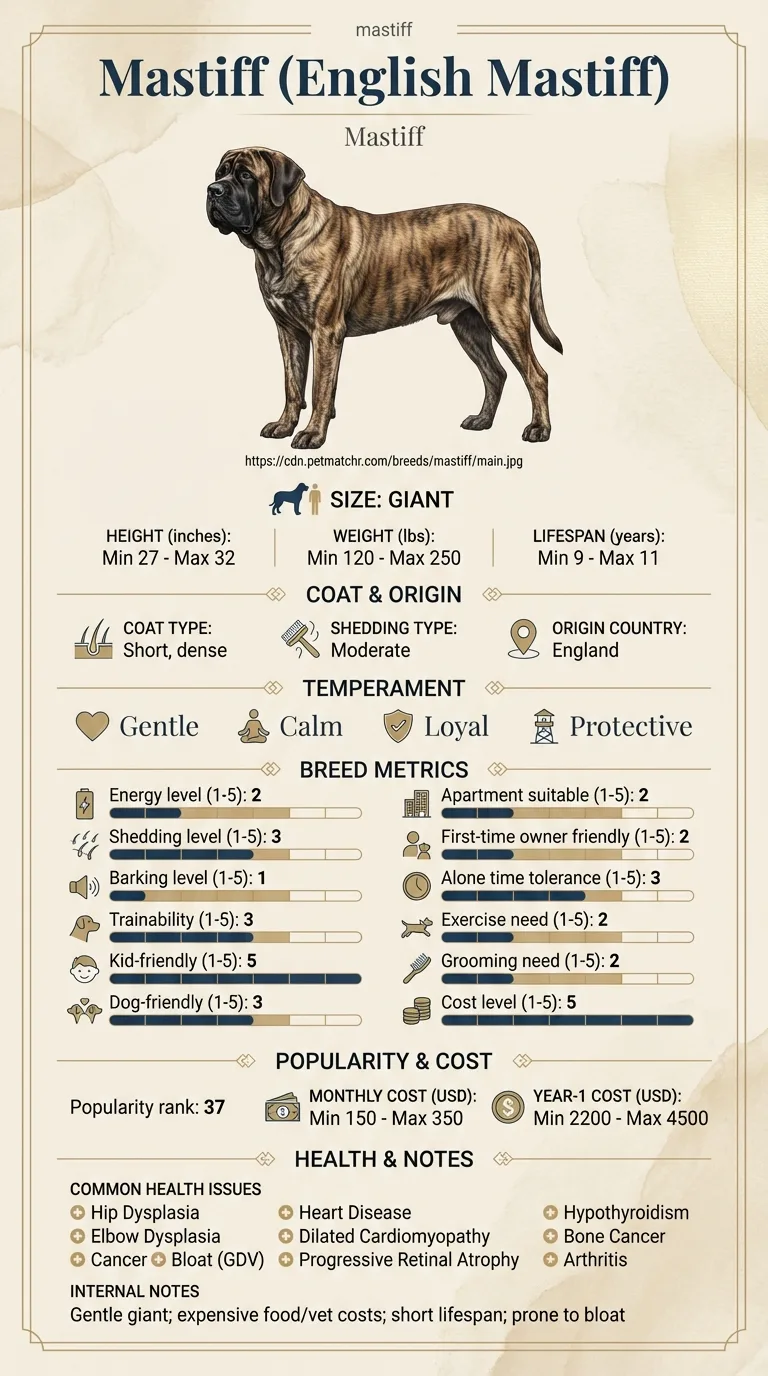
Hip dysplasia appears on the Mastiff's documented health list, and the breed's build explains why the consequences are severe even when the underlying laxity is modest. A dog reaching 120 to 250 pounds transmits far greater force through each hip than a mid-sized breed does, so the same anatomical looseness produces earlier and worse arthritis. Conformation is substantially heritable, which is why screening data exists at all and why breed-level figures carry any signal despite their biases.
Environment factors
The screening data itself is shaped by human behaviour more than by biology. Whether a radiograph is taken, whether it is submitted, at what age, and under which scheme are all owner decisions, and each introduces bias. On the dog's side, the environmental levers are growth-stage feeding, body condition through life, flooring, and the amount of high-impact activity during the first year. A puppy pushed hard for size on slippery floors is running a different risk from a littermate raised leanly on grass.
What you can do at home (once it is not an emergency)
When to talk to your vet
Talk to your vet if you want a baseline assessment, if your puppy has an unusual gait, or if you are unsure how to interpret a certificate a breeder has given you. Book an appointment promptly for bunny-hopping, difficulty rising, reluctance on stairs, or loss of muscle across the hind end. Seek urgent care if your Mastiff suddenly cannot bear weight on a hind limb, cries when the back end is handled, or collapses behind, since a sudden change in a large breed more often indicates an acute injury such as a ruptured cruciate ligament than gradual dysplastic progression.
At home, alongside your vet's plan
Collect and keep copies of both parents' hip certificates before you commit to a puppy, and verify the registered names match the dogs you were shown.
Write down the scoring scheme used, since a grade only means something alongside the system that issued it.
Ask the breeder for feeding guidance in writing and follow a controlled growth plan rather than free-feeding a giant-breed puppy.
Note your own dog's baseline in a file: how it rises, how it climbs stairs, how it sits. Comparison over years is what turns a vague worry into a specific observation.
Arrange insurance before any hip concern is recorded, since orthopaedic conditions become pre-existing quickly once noted.
Formal hip evaluation is normally done at around two years of age, with preliminary films possible earlier. If you are choosing a breeder, expect the research phase to take weeks rather than days; good Mastiff breeders often have waiting lists, and that delay is usually a positive signal. Interpreting your own dog's risk is a lifetime exercise rather than a single answer.
Success here is informational. You bought from a line with documented, verifiable screening, you understand what your dog's own evaluation does and does not cover, and you are not reassured or alarmed by a percentage that was never about your dog. That does not prevent hip dysplasia, but it means every decision you make afterwards is grounded in something real.
Four reasons breed percentages are slippery
Hip dysplasia is genuinely documented in Mastiffs and affects many large breeds, along with some smaller ones such as French Bulldogs. But the specific figure attached to any breed carries several biases worth knowing about.
Submission bias. Registries generally publish data on radiographs that were sent in. Owners and breeders who see obviously terrible hips on the preliminary film often do not submit them, which pushes the published pass rate upward.
Different scoring systems. Some schemes grade hips into categories from excellent to severely dysplastic; others measure joint laxity numerically. A dog rated acceptable under one system may score poorly under another, so figures from different registries cannot be compared directly.
Age at screening. Formal evaluations are usually done at two years, but arthritis develops over a lifetime. A dog certified clear at two can still have painful hips at eight. Prevalence at screening age understates lifetime disease.
Radiographic change versus clinical disease. Many dogs have abnormal hip films and never limp; some dogs with modest changes are visibly uncomfortable. A prevalence figure counts pictures, not suffering, and those two populations overlap only partially.
Population and era. Breed statistics shift over decades as breeding practices change and as screening becomes more or less common, so a figure quoted without a date and a source is close to meaningless.
What to ask a breeder instead of asking for a percentage
A breed-level statistic tells you almost nothing about the specific puppy in front of you. The line matters far more than the breed average, and the information you need is entirely obtainable if you ask precisely.
Ask to see hip evaluation certificates for both parents, with the dogs' registered names on them, the scoring system used and the date. A verbal assurance that the hips are good is not a document. Cross-check names against the paperwork, because certificates for a different dog in the kennel are not unheard of.
Ask about grandparents and about siblings from previous litters. A breeder who tracks outcomes across generations will be able to tell you; one who does not will not. Ask directly whether any dog they have bred has needed hip surgery, and listen to how the answer is given as much as to its content.
Ask what the puppies are being fed and at what rate, because growth-stage nutrition is one of the few environmental factors that genuinely influences hip development in a breed that goes from a few pounds to over a hundred in a year. A breeder pushing maximum growth for size is working against the joints.
Finally, ask what the contract says if the dog is diagnosed later. The answer tells you how seriously the breeder takes their own screening.
Mastiff - What to ask a breeder instead of asking for a percentage
What to do next about hip dysplasia prevalence in Mastiffs
If you think your Mastiff has hip dysplasia prevalence, the plan is three steps: write down what you have seen and when it started, book a veterinary appointment rather than waiting for the next flare, and take video of the behaviour or symptom before you go — the thing you are worried about rarely happens in the consulting room. Screening in the parents covers hip dysplasia, elbow dysplasia, cancer.
What the vet visit should produce is a diagnosis and a written plan, not just reassurance: what is being ruled out, what the monitoring interval is, and which signs mean you come back sooner. Ask what the treatment costs across a year rather than per visit, because that is the number that decides whether you are managing this condition or reacting to it.
Between appointments, keep a short log — dates, what you saw, what changed. It is the single most useful thing an owner brings to a follow-up, and for hip dysplasia prevalence it is often what separates a clear pattern from a guess.
Two certificates and one uncomfortable question
Nadia spent four months looking for a Mastiff puppy and visited three breeders. All three said the parents had good hips. Only two produced certificates when asked, and only one of those had both parents documented under the same scheme with dates and registered names that matched the dogs in the garden.
What decided it was a question she almost did not ask: had any dog from a previous litter needed hip surgery? The breeder she chose said yes — one, six years earlier — and explained which pairing it came from and what she had changed since. The other breeder said no dog she had ever bred had had a single problem.
Nadia's puppy, Wolsey, is now four. His hips have not been formally scored, but he moves well and stays lean. Nadia says the answer she trusted was the one that admitted a failure.
Key takeaway: Breed prevalence figures cannot be applied to an individual puppy, but a breeder's documentation and their willingness to discuss bad outcomes can. A record with one honest problem in it is worth more than a spotless verbal history.
Frequently asked questions
What percentage of Mastiffs have hip dysplasia?
Any single figure you find should be treated as a rough indicator rather than a fact about your dog. Published rates come from voluntarily submitted radiographs and vary by registry, scoring system and era. What is not in doubt is that hip dysplasia is documented in this breed and is common enough that screening is standard practice.
Do hip-scored parents guarantee a healthy puppy?
No, but they shift the odds meaningfully and they tell you the breeder is taking the problem seriously. Hip conformation involves many genes plus growth environment, so good parents can produce an affected puppy and average parents can produce excellent hips. Screening reduces risk; it does not remove it.
Why do small breeds like French Bulldogs also appear in hip dysplasia data?
Because hip dysplasia is about joint conformation rather than size alone. Several small and medium breeds show high rates. What size changes is the consequence: a loose hip on a twenty-pound dog and a loose hip on a two-hundred-pound dog experience very different forces, which is why giant breeds tend to develop symptoms sooner and more severely.
Should I have my own Mastiff's hips screened even if I am not breeding?
It can be worth doing if you want a baseline, particularly if you plan to insure or if your dog shows any early signs. For a pet, the more common approach is to screen when there is a clinical reason. Discuss timing with your vet, since a formal evaluation usually needs sedation and correct positioning to be meaningful.
Does a clear hip score at two years mean my dog is safe for life?
It means the joint looked structurally sound at that point, which is genuinely good news. It does not rule out arthritis developing later from wear, injury or weight gain. Treat it as a strong starting position rather than a lifetime guarantee, and keep managing weight and exercise accordingly.
Is there a DNA test for hip dysplasia?
Not a definitive one. Hip conformation is influenced by many genes and by environment, which is why the standard tool remains a radiograph rather than a cheek swab. Be sceptical of any product that claims to predict hip dysplasia from a genetic test alone.
Why do published hip dysplasia rates vary so much?
They come from voluntary submissions, use different scoring systems, are taken at different ages, and count radiographic change rather than clinical pain. All four inflate or deflate the figure.
Health
What should I ask a Mastiff breeder about hips?
Ask for dated hip certificates on both parents with registered names, ask about siblings and grandparents, ask about puppy feeding rate, and read the health clause in the contract.
Health
Do scored parents guarantee sound hips?
No. They meaningfully improve the odds because conformation is partly heritable, but growth environment and many genes are involved. Screening lowers risk rather than removing it.
Health
Is there a DNA test for hip dysplasia?
No reliable one. Too many genes and too much environmental influence are involved. Radiographs remain the standard assessment.
Health
Does a clear score at two years last for life?
It is a strong starting point, not a guarantee. Arthritis can still develop later from wear, weight gain or injury.
Related DogBreedCompass guides
managing Mastiff hip dysplasia – Covers signs, diagnosis and day-to-day management once dysplasia is present.
Mastiff elbow dysplasia – The front-limb counterpart, also screened by radiograph in this breed.
A fuller vet-visit kit for Mastiff HIP Dysplasia Prevalence
The free prep sheet covers the same-day warning signs, a symptom log and the questions to ask. We are considering a fuller kit that adds a cost worksheet for the usual tests and treatments (US price ranges with their sources) and a plain-English guide to ways of covering the bill. It is not built yet; this list tells us whether it is worth building.
One email, no spam, unsubscribe anytime. Information only, not veterinary advice.