Health
How do I tell regurgitation from vomiting?
Effort and timing. Regurgitation is effortless, gives no warning, produces undigested food, and usually happens within an hour of eating.
Quick answer
How do I tell regurgitation from vomiting?
Effort and timing. Regurgitation is effortless, gives no warning, produces undigested food, and usually happens within an hour of eating.
The link is unexpected but direct: every hard breath a Boston pulls against a narrowed airway tugs on the junction between oesophagus and stomach, and years of that tugging loosens a seal that was meant to stay shut.
Owners whose Boston brings food back up minutes after eating, people who have been told their dog has a hiatal hernia, and anyone trying to work out whether what they are seeing is vomiting or something else.
This guide is not medical advice. If your dog shows pain, sudden behavior change, or worsening symptoms, consult a licensed veterinarian.
Some links may be affiliate links. We may earn a commission at no extra cost to you. We only suggest products we believe are helpful for dog owners.
We research and check what we publish, but we do not warrant that any figure, date, price, or statement is accurate, complete, or current, and we accept no liability for any loss, cost, injury, or other harm arising from the use of this site. Use it as one reference among several. You remain responsible for your own decisions and for your dog's care - confirm anything that matters with a licensed veterinarian or another qualified professional before you act on it. Full disclaimer.
Oesophageal problems in Boston Terriers are largely mechanical in origin. Hard breathing against a restricted airway generates exaggerated negative pressure in the chest, which over time loosens the junction between oesophagus and stomach and allows reflux or a hiatal hernia. The result is effortless regurgitation of undigested food, acid damage to the oesophageal lining, and a risk of material being aspirated into the lungs.
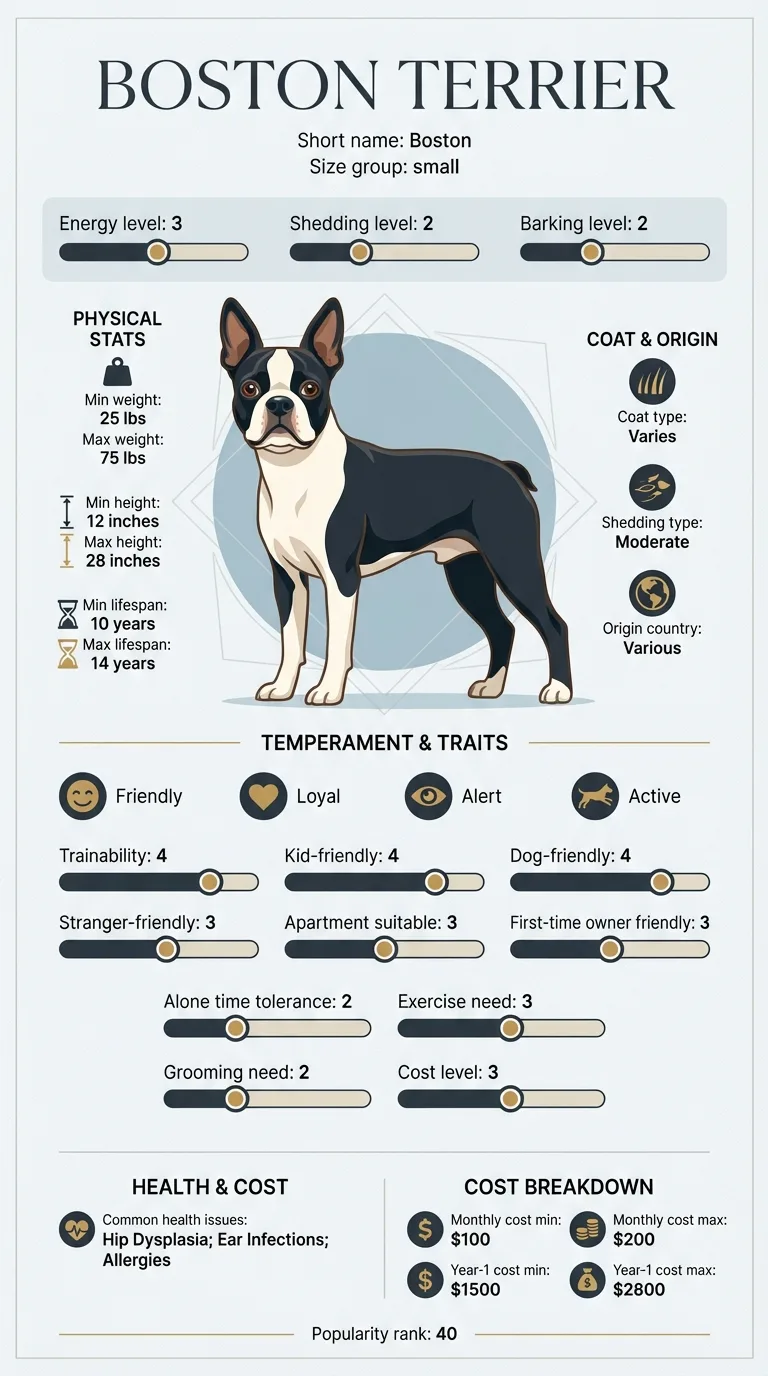
Reflux and regurgitation are common in short-faced dogs generally, and hiatal hernia is recognised as over-represented in brachycephalic breeds. In Boston Terriers, whose airway disease sits at the moderate rather than extreme end, the frequency is lower than in the flattest-faced breeds but the mechanism is identical and worth recognising.
The chain runs from the skull to the diaphragm. A shortened muzzle produces narrowed nostrils and a crowded throat, so each breath requires far more suction, and that suction acts on the junction where the oesophagus passes into the abdomen. Because Bostons vary widely in how obstructed their airways are, they also vary in how much oesophageal trouble they develop - the dogs with the loudest breathing are usually the ones with the most regurgitation, and that association is not a coincidence.
Feeding practice is the main lever an owner holds. Large single meals, competitive fast eating, and exercise immediately after food all raise abdominal pressure at exactly the wrong moment. Heat matters too, because a hot dog pants harder and pants generate the pressures that drive the problem. Households where the dog is fed and then immediately taken out are compressing every risk factor into one window.
Book an appointment for repeated regurgitation, food brought up undigested within an hour of eating, frequent gulping or lip smacking, or unexplained weight loss in a dog that is eating. Seek urgent care if your dog develops coughing, fever, rapid or laboured breathing, or becomes lethargic after an episode of regurgitation - those suggest aspiration pneumonia, which is serious and progresses quickly. Also treat as urgent any dog making repeated unproductive retching efforts with a distended abdomen, which is a different and more immediately dangerous problem.
See all Boston Terrier health problems, which breeds are prone to esophageal disease, or the full Boston Terrier breed guide for temperament, exercise needs and ownership costs.
Feeding changes often reduce episode frequency within one to two weeks. Medication for acid damage typically takes two to four weeks to produce a clear difference. Where airway surgery is part of the plan, improvement in regurgitation is usually apparent within one to three months of recovery. Hiatal hernia sometimes needs its own surgical repair.
A dog that keeps its meals down, maintains a steady weight, has no coughing or chest infections, and no longer needs to be watched anxiously after every dinner. Occasional episodes in a short-faced dog are realistic; daily ones are not.
Owners use the two words interchangeably and vets do not, because they point to entirely different parts of the digestive tract. Describing the correct one changes the whole investigation.
This is the mechanism that connects a Boston Terrier's airway to its digestive tract, and it is worth understanding because it explains why treating one can improve the other.
Breathing in works by lowering the pressure inside the chest so air is drawn down the airway. When that airway is narrowed, the dog must generate a much greater negative pressure to move the same volume of air. Brachycephalic airway syndrome heads this breed's documented health list, so a substantial proportion of Bostons are generating those exaggerated pressures thousands of times a day.
The oesophagus and the top of the stomach sit at the boundary between the chest and the abdomen. A strong negative pressure on the chest side effectively sucks upward on that junction. Over time the hiatus - the opening in the diaphragm - loosens, and part of the stomach can slide up into the chest. That is a hiatal hernia, and it is recognised as being over-represented in short-faced breeds.
Once the seal is compromised, acid moves the wrong way. Refluxed acid inflames the lower oesophagus, which reduces its ability to move food downward, which causes more retention and more reflux.
The practical consequence is that in a dog with both airway obstruction and reflux, correcting the airway often improves the reflux as well - and that reflux medication alone in an untreated airway is treating a symptom of a mechanical problem.

If you think your Boston has esophageal disease, the plan is three steps: write down what you have seen and when it started, book a veterinary appointment rather than waiting for the next flare, and take video of the behaviour or symptom before you go — the thing you are worried about rarely happens in the consulting room. Screening in the parents covers brachycephalic airway syndrome (boas), patellar luxation, cataracts.
What the vet visit should produce is a diagnosis and a written plan, not just reassurance: what is being ruled out, what the monitoring interval is, and which signs mean you come back sooner. Ask what the treatment costs across a year rather than per visit, because that is the number that decides whether you are managing this condition or reacting to it.
Between appointments, keep a short log — dates, what you saw, what changed. It is the single most useful thing an owner brings to a follow-up, and for esophageal disease it is often what separates a clear pattern from a guess.
For three years, Callie's Boston, Hugo, had been on his fourth sensitive-stomach diet. He brought food back up two or three times a week - always within half an hour of eating, always undigested, always without any warning, and he usually ate it again straight away. What finally changed the conversation was Callie describing the timing. Her vet stopped talking about diets and asked how Hugo breathed, which had never come up because his snoring was simply what everyone expected of a Boston. Imaging found a sliding hiatal hernia. The airway examination found a long soft palate and narrow nostrils. Both were addressed at one surgery. Hugo's regurgitation reduced to roughly once a month within three months, on ordinary food. Callie had spent three years and four bags of prescription diet treating a breathing problem through the food bowl.
Key takeaway: In a short-faced breed, food coming back up undigested is often an airway problem in disguise. Get the breathing assessed before the fifth diet change.
Because breathing against a narrowed airway generates exaggerated negative pressure in the chest, which pulls upward on the junction between oesophagus and stomach. Over time that stretches the diaphragmatic opening and weakens the seal.
Part of the stomach sliding upward through the diaphragm into the chest. It can be intermittent, appearing during hard breathing and returning to position afterward, which is why imaging is sometimes done under specific conditions.
The main hazard is aspiration - material entering the airway and reaching the lungs, causing pneumonia. A dog that regurgitates and then develops coughing, fever, laboured breathing or lethargy needs urgent assessment.
For some dogs with oesophageal disease, feeding in an upright position and keeping them upright afterward genuinely helps gravity move food downward. It is a specific therapeutic measure prescribed for particular conditions, not general advice.
It frequently does, because it addresses the pressure mechanism causing the problem. Surgeons often assess and treat both together, and improvement in regurgitation after palate surgery is a commonly reported outcome.
Usually by imaging, sometimes with a contrast study that follows swallowed material down the oesophagus in real time, and sometimes by endoscopy to see the lining directly and assess acid damage.
Food consistency, meal size, feeding position and timing all matter and are often part of the plan. Whether they are sufficient depends entirely on the underlying cause, which is why the diagnosis comes first.
The early signs are set out in the sections above, and they are the reason to book a veterinary appointment rather than wait. Esophageal Disease in Bostons is diagnosed by a vet, not from a symptom list, and the sooner it is on record the more options remain open.
The early signs are set out in the sections above, and they are the reason to book a veterinary appointment rather than wait. Esophageal Disease in Boston Terriers is diagnosed by a vet, not from a symptom list, and the sooner it is on record the more options remain open.
Effort and timing. Regurgitation is effortless, gives no warning, produces undigested food, and usually happens within an hour of eating.
Aspiration pneumonia. Coughing, fever, fast or laboured breathing or lethargy after an episode needs urgent veterinary care.
It contributes substantially. Hard breathing against an obstruction pulls upward on the stomach junction, and correcting the airway often improves the reflux.
Smaller, more frequent meals, a slow feeder, and calm before and after eating. Any change in feeding position should be prescribed rather than guessed at.
A one-page prep sheet for this condition: the signs, the questions to ask, what to get priced. Unlocks here.
You get: Vet visit prep sheet
No spam. One-click unsubscribe. See our privacy policy.
Preview page 1 before you decide.

