Health
How do I know if a white mark on the eye is urgent?
If it appeared suddenly in one eye and the dog is squinting, tearing or rubbing, treat it as urgent. A stable, painless, symmetrical mark is not.
Quick answer
How do I know if a white mark on the eye is urgent?
If it appeared suddenly in one eye and the dog is squinting, tearing or rubbing, treat it as urgent. A stable, painless, symmetrical mark is not.
A white smudge in the middle of the eye that has not changed in six months and does not bother the dog is a different animal entirely from one that appeared on Tuesday.
Owners who have noticed a persistent cloudy mark on the surface of one or both eyes and want to know whether it needs treating, and owners trying to work out whether what they are looking at is an emergency this evening or a topic for the next routine appointment.
This guide is not medical advice. If your dog shows pain, sudden behavior change, or worsening symptoms, consult a licensed veterinarian.
Some links may be affiliate links. We may earn a commission at no extra cost to you. We only suggest products we believe are helpful for dog owners.
We research and check what we publish, but we do not warrant that any figure, date, price, or statement is accurate, complete, or current, and we accept no liability for any loss, cost, injury, or other harm arising from the use of this site. Use it as one reference among several. You remain responsible for your own decisions and for your dog's care - confirm anything that matters with a licensed veterinarian or another qualified professional before you act on it. Full disclaimer.
Corneal dystrophy is the deposition of fat, cholesterol or mineral within the layers of the cornea, producing a white or grey opacity on the front surface of the eye. It is usually present in both eyes in a broadly symmetrical pattern, causes no pain, and progresses slowly if at all. The main clinical task is distinguishing it from conditions that look similar and are urgent.
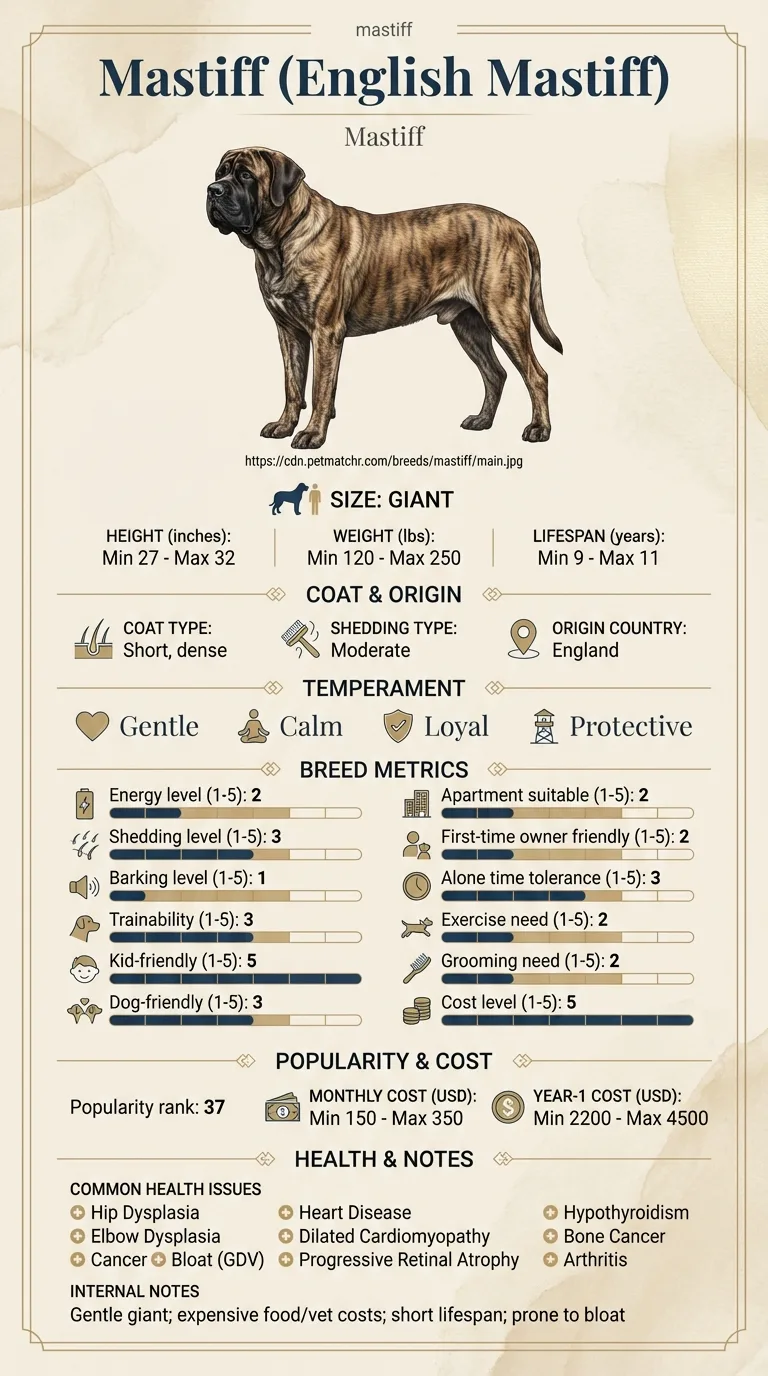
Corneal dystrophy is a recognised condition across a number of breeds but does not appear among the documented eye problems of the English Mastiff, where progressive retinal atrophy is the concern on record. It is included here because white marks on the eye are one of the most common things owners of any breed notice and worry about, and because the distinction between a harmless deposit and an ulcer is genuinely important to get right.
No specific Mastiff predisposition to corneal dystrophy is established, and it would be wrong to claim one. What is relevant about this breed's face is the eyelids. A heavy head with loose, generous facial skin can produce eyelids that sit imperfectly against the eye, and lashes or hair contacting the cornea cause chronic low-grade irritation. That irritation is a genuine cause of corneal change in this kind of dog and is worth checking whenever a corneal opacity is found.
The environment contributes little to primary deposits but a great deal to the conditions confused with them. Long grass, hedgerows, dust, sand and rough play with other dogs cause the corneal scratches and ulcers that owners mistake for a dystrophy. A Mastiff carries its head at a height where branches and undergrowth meet the eye directly, and it does not move quickly enough to avoid them. Dry, heated indoor air can also aggravate an already marginal tear film.
Book an appointment for any new or changing white mark on the eye so it can be stained and identified. Seek same-day or emergency attention if the eye becomes red, if the dog is squinting or holding it shut, if there is discharge, if the dog is rubbing its face persistently, if the surface looks dull, rough or dented rather than smooth, or if the dog shies from light. A corneal ulcer can deepen within hours and a deep ulcer can perforate the eye, which is a sight-threatening emergency. Never put any drop, ointment or home remedy into a painful eye before it has been examined, since some products make ulcers considerably worse.
See all Mastiff health problems, which breeds are prone to corneal dystrophy, or the full Mastiff breed guide for temperament, exercise needs and ownership costs.
Diagnosis takes a single appointment. Once confirmed as a dystrophy, re-examination at six or twelve months is typical, and most dogs show little or no change between visits. Where a metabolic cause is found and treated, any improvement in the deposit is measured over months rather than weeks, and often the deposit simply stops progressing.
Success here is mostly the absence of intervention: a documented, stable, painless deposit, an owner who is no longer anxious about it, and a clear personal rule for what would change the picture. The other half of success is reaction time, so that when the dog does one day develop a genuine corneal ulcer, it is recognised the same day rather than watched for a fortnight.
This is the whole practical value of the topic. Two conditions, similar appearance from a distance, and completely different levels of urgency.
The test that separates these conditions is quick, cheap and available at any general practice, and it is the reason a phone call is never a substitute for an appointment.
Your vet applies a drop of fluorescein stain to the eye. The stain does not adhere to intact cornea, but it does bind to the deeper tissue exposed by an ulcer, which then glows bright green under a blue light. A dystrophy takes up no stain. An ulcer lights up. The answer arrives within a minute of the drop going in.
Alongside that, the vet will look at the deposit's distribution and depth with magnification, check tear production if the eye looks dry, and examine the eyelids. That last part matters more in this breed than owners expect, because a heavy-headed dog with loose facial skin can have subtle eyelid roll or extra lashes contacting the cornea, and a chronically irritated cornea is a cornea that develops problems.
When a genuine dystrophy is confirmed, the usual outcome is that nothing is done. Photographs are taken or measurements noted, and the eye is looked at again in six or twelve months. Treatment is reserved for the minority of cases where the deposit is progressing, where vision is genuinely affected, or where the surface has broken down over a deposit and caused discomfort.
If the deposits are extensive or appeared quickly, your vet may want blood tests. Lipid deposits in the cornea occasionally accompany raised blood fats, which can in turn relate to thyroid disease or other metabolic conditions, and hypothyroidism is documented among the health issues of this breed. That link is worth checking rather than assuming, and it is one of the more useful reasons not to simply dismiss a white patch as cosmetic.

If you think your Mastiff has corneal dystrophy, the plan is three steps: write down what you have seen and when it started, book a veterinary appointment rather than waiting for the next flare, and take video of the behaviour or symptom before you go — the thing you are worried about rarely happens in the consulting room. Screening in the parents covers hip dysplasia, elbow dysplasia, cancer.
What the vet visit should produce is a diagnosis and a written plan, not just reassurance: what is being ruled out, what the monitoring interval is, and which signs mean you come back sooner. Ask what the treatment costs across a year rather than per visit, because that is the number that decides whether you are managing this condition or reacting to it.
Between appointments, keep a short log — dates, what you saw, what changed. It is the single most useful thing an owner brings to a follow-up, and for corneal dystrophy it is often what separates a clear pattern from a guess.
Aled first noticed a small hazy patch in the centre of his Mastiff Fenn's left eye when Fenn was four. It did not seem to bother him. Aled photographed it, took him in, and a fluorescein stain confirmed it was a deposit rather than an ulcer. A matching, smaller patch was found in the right eye that Aled had not spotted. Nothing was done. Aled photographed both eyes every three months and brought the images to Fenn's annual check. Over two years they barely changed. Then one November evening Fenn came back from a walk through a hedge-lined lane holding his right eye half closed and blinking hard. Aled did not photograph it or wait for the morning. He rang the out-of-hours service and went in. It was a corneal ulcer from a thorn scratch, treated and healed within a fortnight. His vet's comment was that Aled's two years of photographs were what let him recognise instantly that this was something different.
Key takeaway: The point of documenting a harmless eye mark is not the mark. It is that you will immediately recognise the day something genuinely wrong appears.
In the great majority of cases, no. The deposit sits within the corneal layers without breaching the surface, so there is nothing to hurt. A dog that is squinting, tearing, rubbing or avoiding light has something else going on and needs examining promptly, regardless of how similar the white patch looks.
Very unlikely. Most deposits are peripheral or small enough that light passes around them. A large central deposit can scatter light and reduce contrast, but progression to functional blindness from dystrophy alone is uncommon. Other causes of vision loss in this breed are more likely culprits if sight is genuinely deteriorating.
Location. A cataract is inside the eye, within the lens, behind the pupil. Corneal dystrophy is on the front surface, in the clear window itself. From a distance both look like white cloudiness, which is why owners confuse them, but a vet with a light distinguishes them instantly.
Usually not. The standard approach is documentation and periodic re-examination. Treatment is considered when a deposit is progressing, when the surface over it breaks down and causes pain, or when an underlying metabolic cause is found that needs addressing in its own right.
It depends on the type and extent of the deposit. Lipid deposits can be associated with raised blood fats, which sometimes reflect thyroid or other metabolic disease. Since hypothyroidism is documented in this breed, a blood panel is a reasonable step for an extensive or rapidly appearing deposit.
No product reliably clears an established corneal deposit, and products marketed for it should be treated with scepticism. Where an underlying metabolic cause is identified and treated, the deposit sometimes stabilises or partially resolves, but that is treating the cause rather than the eye.
Corneal dystrophy is inherited in a number of breeds and tends to appear in young or middle-aged dogs. It is not among the documented eye issues for the English Mastiff, where progressive retinal atrophy is the recognised concern. A dog with corneal dystrophy is worth mentioning to its breeder regardless.
If it appeared suddenly in one eye and the dog is squinting, tearing or rubbing, treat it as urgent. A stable, painless, symmetrical mark is not.
A fluorescein stain. It glows green over an ulcer and does not stick to an intact cornea with a deposit beneath it.
No. A cataract is inside the eye in the lens. Corneal dystrophy is on the front surface. Both look cloudy from across a room.
Usually not. Most cases are documented, photographed and simply re-checked at intervals.
Yes. A dated photograph in consistent light every few months turns a vague impression of change into evidence.
A one-page prep sheet for this condition: the signs, the questions to ask, what to get priced. Unlocks here.
You get: Vet visit prep sheet
No spam. One-click unsubscribe. See our privacy policy.
Preview page 1 before you decide.



