Health
What cardiac disease affects giant breeds most?
Disease of the heart muscle rather than the valves, which typically appears earlier in life than the valve disease seen in small dogs.
Quick answer
What cardiac disease affects giant breeds most?
Disease of the heart muscle rather than the valves, which typically appears earlier in life than the valve disease seen in small dogs.
In a small dog, heart disease usually announces itself with a murmur at ten. In a giant breed it can be well advanced at six with nothing to hear at all.
Owners setting up a sensible health monitoring routine for a Mastiff moving into middle age, and owners whose dog has been found to have a murmur or an irregular rhythm at a routine appointment and want to know what happens next.
This guide is not medical advice. If your dog shows pain, sudden behavior change, or worsening symptoms, consult a licensed veterinarian.
Some links may be affiliate links. We may earn a commission at no extra cost to you. We only suggest products we believe are helpful for dog owners.
We research and check what we publish, but we do not warrant that any figure, date, price, or statement is accurate, complete, or current, and we accept no liability for any loss, cost, injury, or other harm arising from the use of this site. Use it as one reference among several. You remain responsible for your own decisions and for your dog's care - confirm anything that matters with a licensed veterinarian or another qualified professional before you act on it. Full disclaimer.
Cardiac disease in a giant breed usually means the heart muscle itself becoming weaker and the chambers stretching, rather than a valve leaking. The heart pumps less efficiently, fluid backs up into the lungs or the abdomen, and rhythm disturbances develop in the damaged muscle. Early disease is often silent, and the first thing many owners notice is a dog that has quietly stopped doing something it used to do.
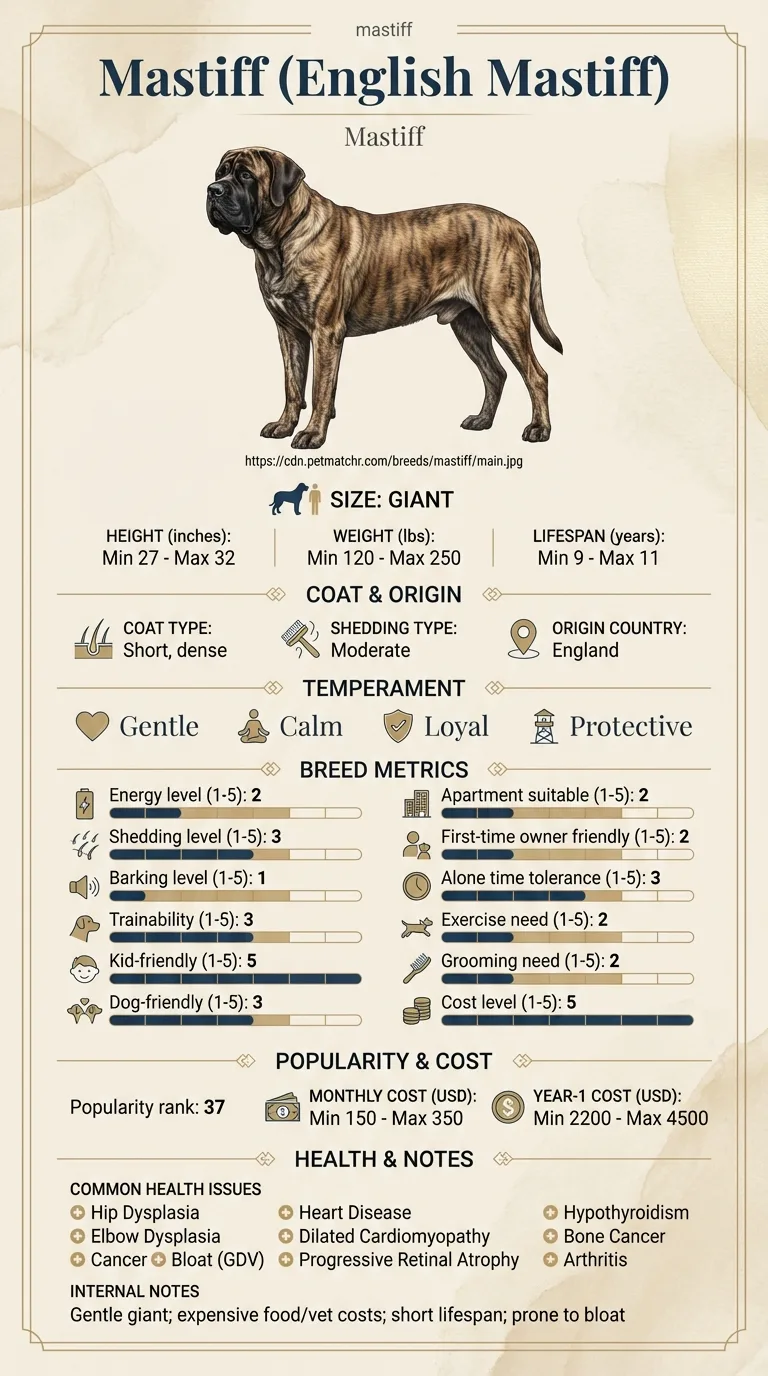
Heart disease and dilated cardiomyopathy both appear on the documented health issue list for the English Mastiff, which places cardiac disease among the handful of conditions any owner of the breed should plan around. Because it tends to develop in middle age rather than late old age, and because the breed lives only nine to eleven years, the window for useful screening is earlier than most owners assume.
Giant breeds are predisposed to disease of the ventricular muscle, and the English Mastiff carries that predisposition explicitly, with both heart disease and dilated cardiomyopathy named among its recognised problems. The mechanism appears to be partly inherited and partly a consequence of scale: a very large heart working against the demands of a body weighing up to a quarter of a ton, in an animal whose whole life is compressed into roughly a decade. Cardiac disease in this breed therefore tends to be a middle-aged rather than a geriatric diagnosis.
Environment does not cause inherited cardiac disease but it determines when it becomes visible and how much reserve the dog has. Excess weight is the largest modifiable factor and adds continuous work. Hot weather, in a breed already handicapped by a shortened muzzle, places extra load on the circulation. High-arousal households produce repeated surges in demand. Diet has been discussed extensively in the context of canine heart muscle disease and any change should be made in consultation with your vet rather than on internet advice.
Book promptly for any fainting or collapse, a rising sleeping breathing rate, a new cough particularly at night, reduced exercise tolerance, or a murmur or irregular rhythm found at a routine check. Go immediately, as an emergency, if your Mastiff is breathing fast and hard while at rest, has blue, grey or very pale gums, coughs up froth or fluid, collapses and does not recover promptly, or has a rapidly swelling abdomen. These indicate heart failure or a major rhythm event and are treatable only with urgent veterinary care. For a dog already diagnosed, agree in advance with your vet what number on the breathing count should trigger a call.
See all Mastiff health problems, which breeds are prone to cardiac disease, or the full Mastiff breed guide for temperament, exercise needs and ownership costs.
From a suspicious finding to a diagnosis is usually two to six weeks including referral. Once medication starts, an improvement in breathing rate and energy is often visible within one to two weeks. Repeat imaging every six to twelve months is standard. Cardiac disease is managed, not cured, and the plan is revised as the condition progresses.
Success is a stable dog: sleeping breathing rate steady and low, appetite and interest intact, still walking its usual route, and no fluid accumulation. In a breed whose natural span is nine to eleven years, a well-managed cardiac patient can spend a substantial part of that span comfortable and normal, which is the honest goal rather than a cure.
Because the pattern of disease differs from small dogs, so should the monitoring. This is a reasonable structure to discuss with your own vet.
Resting respiratory rate is the most useful home cardiac measurement available to any dog owner, and almost nobody does it.
Count the breaths your dog takes while genuinely asleep, over a full sixty seconds, watching the chest rise. One rise and fall is one breath. Do this once or twice a week and write the number down. A healthy dog sleeping in a comfortable room usually sits somewhere below about thirty breaths a minute, and the individual dog's own baseline matters more than any published figure.
The value of this is that fluid accumulating in the lungs, the central problem in developing heart failure, pushes that number up before any owner notices a cough or an intolerance to exercise. A dog whose sleeping rate has climbed from eighteen to thirty over a fortnight has told you something concrete, and it is exactly the kind of information a vet can act on. It also works in reverse: a dog already on cardiac medication whose sleeping rate stays low is a dog whose treatment is working.
There are two other things worth watching in this breed specifically. The first is exercise refusal, which is easy to misread. A Mastiff has genuinely modest exercise needs and a well-earned reputation for lying down, so an owner watching their dog decline a walk may reasonably conclude the dog is being a Mastiff. Compare against the same dog a year ago rather than against any general expectation.
The second is fainting. Brief collapse, a stagger, a dog that goes down and is up again within seconds, is never normal and points strongly at the heart or the airway. It is the single sign most worth acting on, and the one most often dismissed because the dog recovers so completely.

If you think your Mastiff has cardiac disease, the plan is three steps: write down what you have seen and when it started, book a veterinary appointment rather than waiting for the next flare, and take video of the behaviour or symptom before you go — the thing you are worried about rarely happens in the consulting room. Screening in the parents covers hip dysplasia, elbow dysplasia, cancer.
What the vet visit should produce is a diagnosis and a written plan, not just reassurance: what is being ruled out, what the monitoring interval is, and which signs mean you come back sooner. Ask what the treatment costs across a year rather than per visit, because that is the number that decides whether you are managing this condition or reacting to it.
Between appointments, keep a short log — dates, what you saw, what changed. It is the single most useful thing an owner brings to a follow-up, and for cardiac disease it is often what separates a clear pattern from a guess.
Ines started counting her Mastiff Sorrel's sleeping breaths after a vet nurse mentioned it in passing at a routine appointment. Sorrel was five, entirely well, and the number sat between sixteen and nineteen for eleven months. Ines put it in a spreadsheet on Sunday evenings, mostly out of habit. In the twelfth month the figure went to twenty-four, then twenty-eight, then thirty-one over three weeks. Sorrel had no cough, was eating normally, and had not refused a walk. Ines rang the practice anyway and brought the spreadsheet. The examination found a soft murmur that had not been present before. The echocardiogram that followed identified early changes in the heart muscle, well before any fluid had accumulated. Sorrel started medication, and her sleeping rate returned to the low twenties within a fortnight. Her cardiologist told Ines that most dogs arrive at that appointment already in failure, and that a year of Sunday evening numbers had bought Sorrel a considerable head start.
Key takeaway: One minute a week with a sleeping dog produces the only cardiac data an owner can gather at home, and it frequently notices trouble before the dog or the stethoscope does.
For degenerative mitral valve disease, yes, that pattern is real and small breeds dominate it. It is not the whole picture. Large and giant breeds are more prone to disease of the heart muscle itself, which tends to appear earlier in life, and heart disease is documented among the health issues of the English Mastiff.
There is no single rule, and it should be an individual decision with your vet. Many cardiologists would consider a baseline echocardiogram in a giant breed around middle age, roughly five or six, and sooner if there is any family history, murmur, arrhythmia or symptom.
A murmur is a finding, not a diagnosis. It grades from trivial to severe and can arise from several causes, some of which need nothing at all. The next step is usually an echocardiogram, which distinguishes between them, and that is a far more informative test than repeat listening.
Yes, and this is the crux of the issue in giant breeds. Disease of the heart muscle often produces no murmur, and arrhythmias are intermittent. A dog can have significant early muscle disease with a completely normal consultation, which is why symptoms carry more weight than a clean examination.
It can indicate fluid on the lungs from heart failure, but in this breed it may equally reflect airway anatomy or a respiratory infection. A soft persistent cough, particularly at night or after lying down, combined with a rising sleeping breathing rate, points towards the heart and needs prompt assessment.
Generally yes once heart disease is established, with the dose adjusted over time as the condition progresses. In a giant breed the drug quantities are large and the ongoing cost is significant, which is worth understanding at the outset rather than discovering at the third repeat prescription.
Usually yes, in a modified form, and your cardiologist will set the limits. Gentle regular activity is generally better than either enforced rest or unrestricted exertion. What should be avoided is sudden intense excitement, heat, and being pushed beyond the dog's own pace.
Disease of the heart muscle rather than the valves, which typically appears earlier in life than the valve disease seen in small dogs.
Count chest rises for a full minute while the dog is asleep, once or twice a week, and record it. A rising trend is an early warning.
Yes. Brief collapse with full recovery is never normal and should be investigated promptly, even if the dog seems perfectly well afterwards.
Cardiologist echocardiograms on both parents, with dated certificates, plus honest longevity information across the wider family.
Yes. Excess weight adds workload to a compromised heart and worsens breathing, so weight control is part of every cardiac management plan.
A one-page prep sheet for this condition: the signs, the questions to ask, what to get priced. Unlocks here.
You get: Vet visit prep sheet
No spam. One-click unsubscribe. See our privacy policy.
Preview page 1 before you decide.



