Health
What is the most urgent sign?
Back legs that stop working, or a dog that cannot stand. That is an emergency the same hour, and the nearest hospital with imaging and surgery is where to go.
Quick answer
What is the most urgent sign?
Back legs that stop working, or a dog that cannot stand. That is an emergency the same hour, and the nearest hospital with imaging and surgery is where to go.
The difference between a dog that walks again and a dog that does not is often measured in hours, and the clock starts the moment the back legs stop working properly.
Owners who came home to a Boston that will not get out of its bed, people whose dog yelped jumping off a chair and then went quiet and hunched, and anyone weighing surgery against conservative management with a stopwatch running.
This guide is not medical advice. If your dog shows pain, sudden behavior change, or worsening symptoms, consult a licensed veterinarian.
Some links may be affiliate links. We may earn a commission at no extra cost to you. We only suggest products we believe are helpful for dog owners.
We research and check what we publish, but we do not warrant that any figure, date, price, or statement is accurate, complete, or current, and we accept no liability for any loss, cost, injury, or other harm arising from the use of this site. Use it as one reference among several. You remain responsible for your own decisions and for your dog's care - confirm anything that matters with a licensed veterinarian or another qualified professional before you act on it. Full disclaimer.
Intervertebral disc disease is the sudden failure of a cushioning disc between two vertebrae, pushing material into the spinal canal and compressing the cord. In Boston Terriers it presents as abrupt back or neck pain, a hunched posture, and in worse cases hind-limb weakness or paralysis. It is a genuine emergency at the severe end, and the speed of the response strongly influences whether the dog walks again.
Uncommon in Boston Terriers compared with the classic disc breeds, and not part of the breed's core documented health profile. When it does happen, however, it happens the same way and with the same urgency, and owners of a breed not known for it are often slower to recognise what they are looking at.
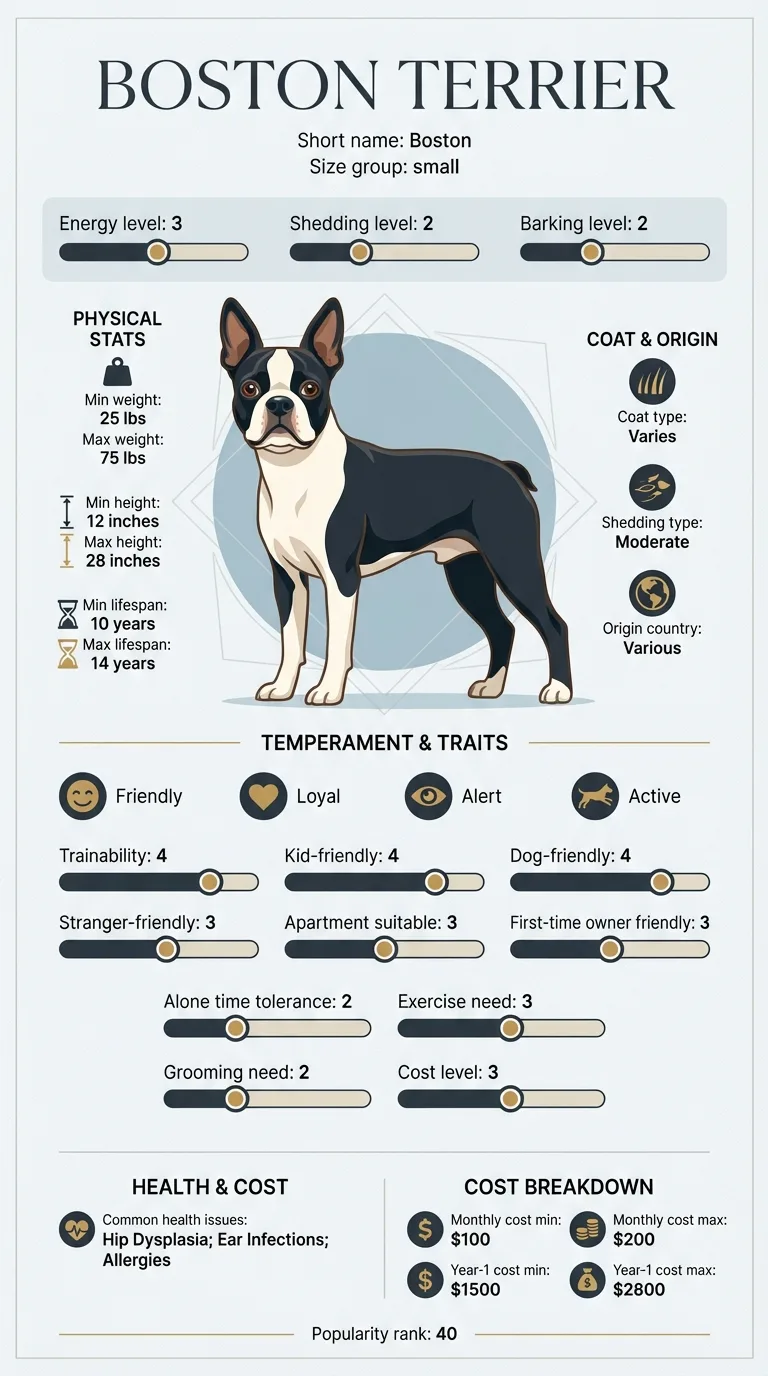
Premature disc hardening is genetically driven and concentrated in breeds carrying particular short-limb variants. Boston Terriers show it far less than the breeds it defines, but a compact, muscular body of 12 to 25 pounds still generates real force when it launches off furniture, and a lively, comical temperament means these dogs launch off furniture a great deal. Their strong trainability is an advantage here: a Boston can genuinely be taught to use a ramp.
Homes are the risk environment. Sofa-height furniture, beds a dog jumps down from at speed, hard flooring with no grip, and stairs taken at a run all supply the loading event. Weight gain multiplies every one of those forces. A dog kept on a rug-lined route with ramps to its favourite furniture is meaningfully less exposed than one that hurls itself off a bed twenty times a day.
Sudden back or neck pain, a hunched or tense posture, yelping on being lifted, or shivering with no other explanation all warrant a same-day appointment. Treat it as an immediate emergency, day or night, if your Boston cannot stand, drags a back leg, scuffs the tops of the back paws, becomes incontinent, or loses feeling in the hind limbs. Phone ahead and ask whether the practice can perform advanced imaging and spinal surgery, because if it cannot you need to be driving to somewhere that can.
See all Boston Terrier health problems, which breeds are prone to backspine issues, or the full Boston Terrier breed guide for temperament, exercise needs and ownership costs.
Conservative management means four to six weeks of strict confinement, with improvement usually visible in the first fortnight. Post-surgical recovery runs six to twelve weeks with structured rehabilitation. Dogs that lose deep pain sensation face a much longer and less certain road, and some do not regain walking.
Success depends where you started. From pain-only, it is a dog that is comfortable and back to normal activity within a restructured home. From paralysis, it is independent walking and continence, even if the gait never looks quite the same again.
Vets grade disc disease by neurological function, and the grade is what determines both urgency and prognosis. Recognising roughly where your dog sits helps you communicate on the phone, though the formal assessment is a vet's job.
Stop the dog moving. This is counter-intuitive because a painful dog often still wants to follow you around, and every step risks displacing more disc material. Confine it - a crate, a carrier, a small room without furniture to climb.
Lift with two hands, one under the chest and one under the pelvis, so the spine stays level rather than folding. Do not scoop a Boston up under the front legs. If a carrier is available, that is the safest way to travel.
Phone ahead rather than turning up. A practice that cannot image or operate will need to refer you, and knowing that before you get in the car saves an hour you may not have.
Do not give human painkillers. Several are seriously toxic to dogs, and some make surgical anaesthesia riskier if it is needed within the day.

If you think your Boston has back/spine issues, the plan is three steps: write down what you have seen and when it started, book a veterinary appointment rather than waiting for the next flare, and take video of the behaviour or symptom before you go — the thing you are worried about rarely happens in the consulting room. Screening in the parents covers brachycephalic airway syndrome (boas), patellar luxation, cataracts.
What the vet visit should produce is a diagnosis and a written plan, not just reassurance: what is being ruled out, what the monitoring interval is, and which signs mean you come back sooner. Ask what the treatment costs across a year rather than per visit, because that is the number that decides whether you are managing this condition or reacting to it.
Between appointments, keep a short log — dates, what you saw, what changed. It is the single most useful thing an owner brings to a follow-up, and for back/spine issues it is often what separates a clear pattern from a guess.
Callum's five-year-old Boston, Rufus, came off the back of the sofa after a doorbell and landed badly. He yelped once, then stood very still with his back arched and refused to sit down. At the practice that afternoon, the neurological examination found pain but no weakness - the mildest grade. The recommendation was strict confinement and pain relief, and Callum admits he thought that sounded easy. It was not. Six weeks of a pen in the living room, lead-only toilet trips, and a dog whose whole personality is enthusiasm. Twice Callum let him have the run of the kitchen and twice the hunching came back the following day. Rufus recovered fully. The sofa now has a ramp bolted to the end of it, and Callum's advice to anyone in the same position is that half-rest is not rest.
Key takeaway: Confinement is the treatment, not the waiting room before the treatment. Dogs that fail conservative management usually failed the confinement.
They sit well below the classic high-risk breeds such as Dachshunds and Beagles. The Boston's own documented health list centres on airway disease, patellar luxation, cataracts, corneal ulcers and deafness. Disc disease happens in this breed but is not its signature problem.
Often something mundane - jumping down from a bed, twisting hard in play, landing awkwardly off a step. The disc has usually been degenerating for months or years; the jump is only the final load.
No. Dogs with pain only, or mild wobbliness, are often managed with strict confinement and pain relief for several weeks. Loss of the ability to walk shifts the balance strongly toward surgery, and that decision is time-sensitive.
Crate or pen confinement with lead-only toilet breaks, for four to six weeks. Not 'quiet time in the house'. Partial rest is the most common reason conservative management fails.
Dogs that have had one episode have a meaningfully higher chance of another, because the disc changes affect the whole spine rather than a single level. Long-term management is about reducing loading, not returning to normal habits.
A harness protects the neck and prevents the sharp jerks a collar transmits, which is worth doing. It cannot prevent a thoracolumbar disc from extruding during a jump, so it is one measure among several.
Neurological examination localises the lesion; MRI or CT confirms which disc and how much compression there is. Plain X-rays cannot show a disc pressing on the cord and are used mainly to exclude other causes.
Back legs that stop working, or a dog that cannot stand. That is an emergency the same hour, and the nearest hospital with imaging and surgery is where to go.
One hand under the chest, one under the pelvis, keeping the spine level. Never lift under the front legs alone.
Spinal imaging and surgery is one of the largest bills in small animal practice, typically several thousand, and it usually arrives without warning. This is the scenario insurance exists for.
Ramps instead of jumps, non-slip flooring, a harness, a lean bodyweight, and an end to games built around twisting and leaping.
A one-page prep sheet for this condition: the signs, the questions to ask, what to get priced. Unlocks here.
You get: Vet visit prep sheet
No spam. One-click unsubscribe. See our privacy policy.
Preview page 1 before you decide.


